
Patient Information
Coronary Angiography
& Intervention
This page explains what to expect from cardiac catheterisation, the potential benefits and risks of both diagnostic angiography and coronary intervention, and how to prepare. Please read it carefully before your procedure and bring any questions to your pre-procedure consultation with Dr Nijjer.
This page does not replace a signed consent form. A formal consent discussion will take place with Dr Nijjer or a member of his team before any procedure is performed. You may withdraw consent at any time, including after this page has been read and before the procedure begins.
A
What Is Involved
Cardiac Catheterisation &
Coronary Angiography
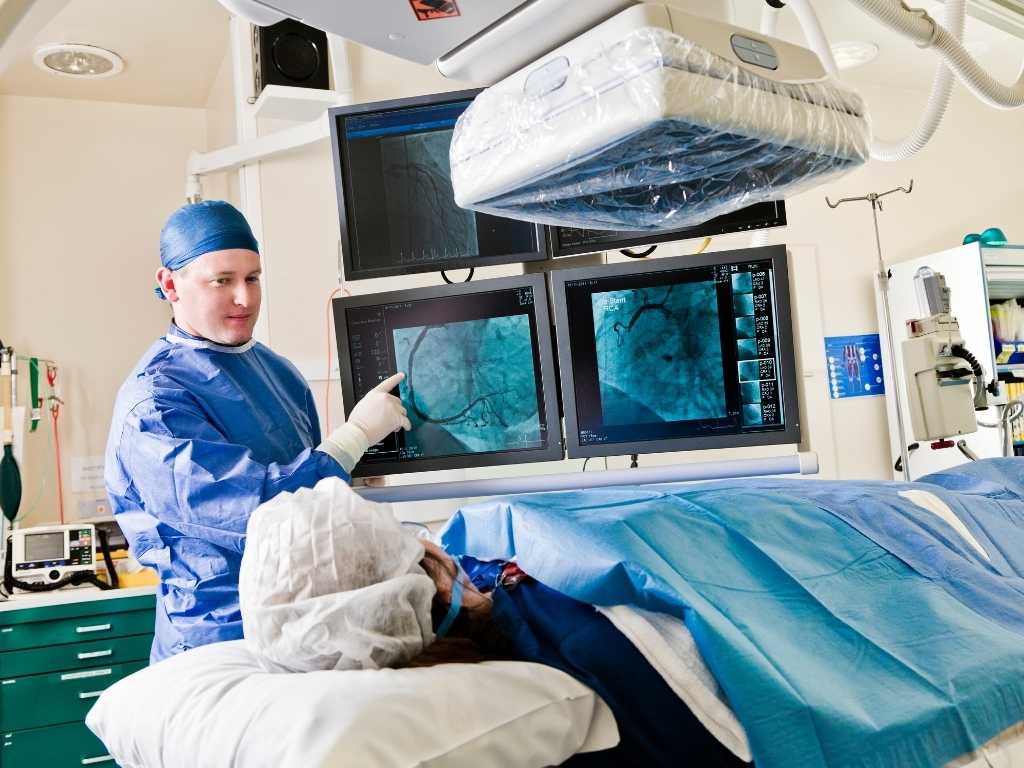
Coronary angiography — also called cardiac catheterisation — is a procedure in which a fine, flexible tube (catheter) is passed through an artery, usually at the wrist or groin, and guided under X-ray towards the heart. A small amount of contrast dye is then injected directly into the coronary arteries, producing detailed moving images of their internal structure. This allows Dr Nijjer to see the precise location and severity of any narrowings or blockages.
The procedure is performed in a specially equipped catheterisation laboratory under local anaesthetic, with light sedation available if you prefer. You will be awake throughout but comfortable. The diagnostic part of the procedure typically takes 20–40 minutes. You will be able to eat and drink normally immediately afterwards.
Radial access (wrist) is Dr Nijjer's preferred approach and is used in most cases. A small sheath is placed in the radial artery at the wrist; the risk of access-site bleeding and haematoma is substantially lower by this route than by the traditional femoral (groin) approach, and you can sit up and mobilise almost immediately. Femoral access is used when radial access is not possible.
Diagnostic vs Interventional
What May Happen During the Procedure
In many cases, the angiogram is planned as a purely diagnostic procedure — the purpose is to gather information about the coronary anatomy and report the findings to you and your referring team. No treatment is performed in the same sitting.
In some cases, if a significant narrowing is found at angiography, Dr Nijjer may recommend proceeding to coronary intervention in the same session — rather than bringing you back for a second procedure. This decision is discussed with you before the procedure begins, or — if a finding is unexpectedly significant — explained and agreed with you in the catheterisation laboratory at the time.
Additional tests may be performed alongside angiography when clinically indicated. A pressure wire (iFR or FFR) measures whether a narrowing is truly limiting blood flow. Intracoronary imaging (IVUS or OCT) provides detailed cross-sectional pictures of the vessel wall. Both assessments use the same arterial access as the angiogram and add a modest amount of time to the procedure.
Staged procedures. If intervention is planned in advance, Dr Nijjer will have already discussed the findings and the proposed treatment with you at a prior consultation. If intervention is deferred to a separate procedure after a diagnostic angiogram, the decision and its rationale will be explained at your follow-up appointment.
Understanding the Risks
Overall Procedure Risk
All medical procedures carry some risk. For cardiac catheterisation the risks are well-characterised, low in absolute terms, and managed by an experienced team with equipment immediately available to deal with any complication. The risk level depends on whether the procedure is diagnostic only, or includes coronary intervention.
Diagnostic Angiography Only
1
1,000
Risk of a serious complication
Risks that apply
- Bruising and haematoma at the access site
- Significant bleeding requiring prolonged pressure
- Injury to the access artery (wrist or groin)
- Coronary artery dissection or perforation
- Heart attack (myocardial infarction)
- Stroke or transient ischaemic attack
- Emergency surgery
- Death
- Contrast allergic reaction
- Contrast-related kidney impairment
With Coronary Intervention, Pressure Wire or Imaging
1
100
Risk of a serious complication
Same risks apply — at higher frequency
- Bruising and haematoma at the access site
- Significant bleeding requiring prolonged pressure
- Injury to the access artery (wrist or groin)
- Coronary artery dissection or perforation
- Heart attack (myocardial infarction)
- Stroke or transient ischaemic attack
- Emergency surgery
- Death
- Contrast allergic reaction
- Contrast-related kidney impairment
These figures represent population averages for patients undergoing elective procedures. Your individual risk may be higher or lower depending on your age, medical history, kidney function, and the complexity of your coronary anatomy. Dr Nijjer will discuss your personal risk profile with you before any procedure and will document any specific additional risk factors on your consent form.
Risks Explained
Individual Risks in Detail
The risks below apply to both diagnostic and interventional procedures. The frequency of each risk is higher when coronary intervention is performed. "Common" means it occurs in more than 1 in 100 patients; "uncommon" in 1–10 per 1,000; "rare" in fewer than 1 per 1,000.
Bruising & Haematoma
Discolouration and swelling at the wrist or groin access site is the most frequent minor complication. Blood may collect under the skin forming a firm lump (haematoma), which can be tender for several days. It resolves on its own in the majority of cases without requiring treatment.
Significant Bleeding
Heavier bleeding at the access site may require prolonged manual pressure, a compression device, or a closure device placed in the artery. Bleeding requiring a blood transfusion is very uncommon. The radial (wrist) approach carries a substantially lower bleeding risk than the femoral (groin) approach.
Access Artery Injury
Damage to the radial artery at the wrist or the femoral artery at the groin can cause narrowing, spasm, or a false aneurysm (pseudoaneurysm). Radial artery occlusion occurs in up to 2–5% of radial procedures but the hand circulation is almost always maintained through other vessels and rarely causes symptoms.
Coronary Artery Dissection
A dissection is a tear in the inner lining of the coronary artery, caused by catheter, guidewire, or balloon contact. Small dissections at the edge of an intervention site are common and usually benign. Larger dissections that impair blood flow require prompt treatment to prevent a heart attack.
Coronary Artery Perforation
A perforation is a small hole in the coronary artery wall, allowing blood to leak into the space around the heart (pericardium). This can cause the heart to be compressed — a serious but manageable complication. Perforations are most commonly caused by guidewires during complex intervention in calcified arteries.
Heart Attack (Myocardial Infarction)
A heart attack during the procedure can be caused by a coronary artery closing suddenly due to spasm, dissection, thrombosis, or material displaced from a plaque. Small procedure-related myocardial infarctions — detectable only on blood tests — are more common than clinically significant events, particularly during complex intervention in calcified arteries.
Stroke or TIA
A stroke can occur if a blood clot or fragment of atherosclerotic plaque dislodges during catheter manipulation and travels to a brain artery. The risk is very low in elective procedures but is higher in patients with atrial fibrillation, significant aortic atherosclerosis, or previous stroke. A transient ischaemic attack (TIA) produces similar symptoms that resolve fully within 24 hours.
Emergency Surgery
In rare circumstances — most commonly a large coronary perforation or uncontrolled dissection that cannot be managed with catheter-based techniques — emergency referral for coronary artery bypass surgery is required. This is an extremely unusual outcome of modern catheter-based procedures but remains a possibility that must be disclosed.
Death
Death as a direct result of elective cardiac catheterisation is very rare in carefully selected patients. The risk is significantly higher in patients having emergency procedures, those with severely impaired cardiac function, or those with very complex anatomy. In the elective setting the risk is approximately one in a thousand for diagnostic procedures and somewhat higher when complex intervention is performed.
Contrast Reaction & Kidney Effects
Iodine-based contrast dye used in all coronary angiography procedures can cause an allergic reaction, ranging from mild flushing and nausea to, very rarely, a severe anaphylactic reaction. In patients with pre-existing kidney disease, contrast dye can temporarily worsen kidney function. All patients at risk are identified beforehand and protective measures taken.
Abnormal Heart Rhythm
Brief disturbances of heart rhythm are common during catheter manipulation inside the heart and are usually transient and harmless. Occasionally a sustained arrhythmia — such as ventricular fibrillation — requires treatment. ECG is monitored continuously throughout every procedure and a defibrillator is always immediately available.
Radiation Exposure
Coronary angiography uses ionising radiation (X-rays) to produce images. The dose varies with procedure complexity but is typically 2–10 mSv — equivalent to several months to a few years of natural background radiation. For a single procedure this represents a very small theoretical increase in lifetime cancer risk. Radiation exposure is minimised at all times. Angiography is not performed during pregnancy.
Before & After
Preparation & Aftercare
Before Your Procedure
- Fasting: Do not eat for at least four hours before your procedure. You may drink clear fluids (water, black tea or coffee without milk) up to two hours before.
- Medications: Continue all regular medications with a small sip of water on the morning of the procedure unless specifically told otherwise by Dr Nijjer or his team. Important exceptions are listed below.
- Metformin (for diabetes): Stop metformin 48 hours before the procedure if you have any degree of kidney impairment. This will be specified in your pre-procedure letter.
- Anticoagulants (warfarin, DOACs): You will receive specific instructions about whether to stop these. Do not stop anticoagulants without explicit instruction — the timing depends on your reason for taking them.
- Insulin and diabetic medications: Do not take your morning insulin or oral hypoglycaemic agents on the day of the procedure. Monitor your blood glucose. Your diabetes nurse or team can advise.
- Pregnancy: Please inform Dr Nijjer's team immediately if there is any possibility you may be pregnant. The procedure uses ionising radiation and contrast dye, both of which require specific consideration.
- Allergies: If you have had a previous reaction to contrast dye or iodine, inform the team well in advance — pre-medication can be arranged.
- What to bring: Your NHS number, a list of all current medications and doses, any recent blood test results or imaging, and a companion to accompany you home if sedation is planned.
After Your Procedure
- Radial (wrist) access: A compression band is applied to the wrist for 2–4 hours. You may sit up, eat, and drink immediately after the procedure. You may be discharged the same day in most cases.
- Femoral (groin) access: You will need to lie flat for at least two hours while the access site is closed with pressure or a closure device. You may be kept overnight for observation.
- Driving: Do not drive for 24 hours after the procedure. If you have received intravenous sedation, do not drive for 48 hours. Arrange for someone to drive you home.
- Physical activity: Rest on the day of the procedure and avoid strenuous activity for 48 hours. Avoid heavy lifting or vigorous exercise for 3–5 days.
- Access site care: Keep the wrist or groin site clean and dry. Some bruising is expected and normal. A firm lump (haematoma) at the access site is common and will gradually resolve over 2–4 weeks.
- Medications: If coronary intervention was performed and a stent was placed, you will be prescribed dual antiplatelet therapy (typically aspirin plus ticagrelor or clopidogrel). It is essential not to stop these medications without consulting Dr Nijjer first.
- Results and follow-up: Dr Nijjer will discuss the findings with you before discharge. A follow-up appointment will be arranged to review your result, adjust medications, and plan next steps.
Seek immediate medical attention (call 999 or go to A&E) if after discharge you experience: heavy or expanding bruising at the access site, a pulsating lump at the wrist or groin, chest pain, breathlessness at rest, weakness on one side of the body, difficulty speaking, sudden visual disturbance, or collapse. Call 999 immediately — do not wait.
Your Rights & Questions
Before You Consent
Questions to Ask Dr Nijjer
You have the right to ask any questions about your procedure before you sign a consent form. No question is too minor. The following may be helpful as a starting point:
- Why do I need this procedure, and what happens if I choose not to have it?
- Will you be performing the procedure yourself, or will a colleague?
- Are there any specific risks that apply to me based on my medical history?
- Is there a real chance you will need to proceed to intervention on the same day, and how will I be involved in that decision?
- What does the result of this procedure mean for my long-term treatment?
- How many of these procedures have you personally performed?
- Are there alternative investigations I could have instead?
- Can I have a copy of the consent form to take home and read before my admission?
Your Right to Withdraw Consent
You may change your mind about having the procedure at any time — including after signing the consent form, and including after arriving in the catheterisation laboratory. Your consent is voluntary and can be withdrawn without prejudice to your future care.
If you have questions before or after your procedure, or if you wish to discuss the risks and benefits in more detail, please contact Dr Nijjer's team directly:
Phone: 0203 983 8001
Email: ella@oneheartclinic.com
Address: One Heart Clinic, 68 Harley Street, London W1G 7HE
We aim to respond to all enquiries within one working day. For urgent clinical concerns after a procedure, please call 999 or attend your nearest A&E.
Speak to Dr Nijjer Before Your Procedure
Dr Nijjer's team is available to answer any questions about your upcoming procedure, discuss your individual risk profile, or arrange a pre-procedure consultation.